
To Buy Abilify Online Visit Our Pharmacy ↓
 Abilify Vs Other Antipsychotics: Key Differences
Unique Mechanism: Abilify's Partial Dopamine Agonist Action
I remember the first time a colleague described it as a molecular dimmer switch: instead of turning dopamine signaling fully on or off, this medication nudges receptors toward balance. By partially stimulating D2 receptors when levels are low and dampening activity when levels are high, it can reduce hallucinations and delusions without provoking the same degree of movement problems associated with stronger blockers. That calibrated action also tends to spare prolactin elevation, offering a different side effect profile compared with traditional antagonists.
Clinically, this nuanced pharmacology can translate into fewer extrapyramidal symptoms for some patients and a lower tendency for metabolic hormone disruption, though individual responses vary. Choosing this agent often reflects a trade-off: seeking behavioral control with potentially reduced movement risk while monitoring for activation or akathisia.
| Feature | Implication |
|---|---|
| Partial agonism | Stabilizes dopamine |
| EPS | Lower risk |
| Prolactin | Reduced elevation |
Comparing Side Effects: Movement, Weight, Metabolic Risks
Clinicians often tell patients that antipsychotics differ markedly in how they affect movement: some older agents can cause stiff limbs, tremor, or the distressing inner restlessness known as akathisia. Abilify’s partial dopamine agonism generally reduces the risk of classic extrapyramidal symptoms compared with high‑potency typicals like haloperidol and some risperidone doses, but it can still provoke akathisia in sensitive individuals, so careful dose titration and monitoring remain essential.
Weight gain and metabolic effects form a different trade‑off: medications such as olanzapine and clozapine are notorious for rapid weight increase, dyslipidemia and diabetes risk, whereas abilify is typically more weight‑neutral and shows lower rates of metabolic disturbance in cohorts, though exceptions occur. Choosing a drug requires balancing symptom control with baseline cardiometabolic risk, lifestyle support, and routine labs; shared decision‑making helps tailor treatment and supports long‑term adherence and frequent monitoring strategies.
Efficacy Differences Across Schizophrenia, Bipolar, Depression Augmentation
Clinicians often find that abilify’s partial dopamine agonism produces antipsychotic efficacy comparable to many second‑generation agents for acute psychosis and relapse prevention in schizophrenia, with particular benefits for positive symptoms and lower risks of hyperprolactinemia and sedation. However, responses vary; some patients with prominent negative symptoms or treatment‑resistant illness may require different agents or clozapine, and head‑to‑head trials show modest differences in overall symptom reduction rather than clear superiority.
In bipolar disorder abilify is effective for acute mania and as maintenance therapy for preventing mood episodes, often chosen for tolerability advantages. As adjunctive treatment in major depressive disorder it produces small-to-moderate additional benefit when antidepressants alone are inadequate, with clinical gains that can emerge within weeks. Ultimately, comparative efficacy is shaped by patient history, symptom profile and tolerability — so personalized selection trumpets average trial results and careful metabolic monitoring.
Dosing, Formulations, and Adherence: Pills Versus Injections
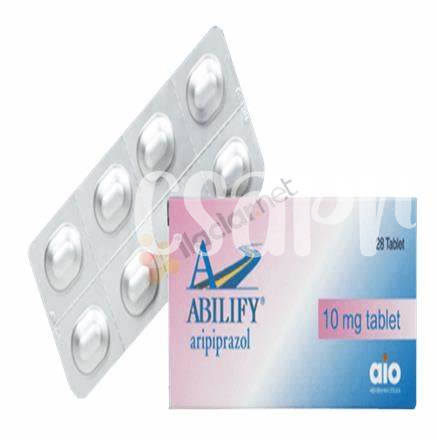
Some mornings the routine is a tablet, other days a clinic visit replaces it; patients describe relief and convenience differently. abilify's oral tablets allow flexible titration and immediate stops, which suits people starting treatment or adjusting doses under clinician guidance.
Long-acting injections, by contrast, free many from daily reminders and reduce relapse risk via steady plasma levels. They require scheduled appointments, but for people with adherence challenges predictable pharmacology and less frequent dosing can improve outcomes and quality of life.
Choosing between tablet or injection balances side-effect monitoring, need for titration, and access barriers like clinic travel or insurance. Shared decision-making remains essential: clinicians weigh individual patient preference, stability, and adherence to tailor optimal regimens.
Pharmacokinetics and Interactions: Cyp Activity and Implications
Understanding drug metabolism can feel like learning a new language, but it’s crucial when choosing antipsychotics. Abilify’s active ingredient is metabolized largely by CYP2D6 and CYP3A4, so inhibitors or genetic poor-metabolizer status can raise levels, altering efficacy and side-effect risk.
Clinically, watch for CYP blockers (e.g., fluoxetine) or inducers (e.g., carbamazepine) that change dosing.
| Enzyme | Implication |
|---|---|
| CYP2D6/CYP3A4 | Alters abilify levels |
That means clinicians often adjust doses, choose alternatives, or monitor drug levels and metabolic signs. Genotype-guided prescribing can clarify risk for poor metabolizers, while vigilance for CYP inhibitors or inducers prevents unintended toxicity or treatment failure. Clear communication with patients about over-the-counter and herbal interactions completes safe management. Education and periodic review remain essential to balance benefits against interaction risks when using abilify alongside other medications. Tailored plans reduce harm and improve outcomes consistently
Cost, Accessibility, and Individualized Treatment Decision Factors
Deciding between medications often means balancing sticker price, insurance coverage, and local availability. A newer brand-name option may offer better tolerability but higher co-pays; generics increase affordability and adherence. Clinic formularies, prior authorization hurdles, and the presence of long-acting injections at nearby pharmacies shape what treatments are realistically achievable for each patient.
Clinicians weigh efficacy, side-effect profiles, medical comorbidities, and drug interactions against a person’s lifestyle and treatment goals. Smoking, hepatic function, and concomitant medications alter choices; so do pregnancy plans and cognitive demands. Open dialogue about priorities, prior responses, and barriers to adherence allows pragmatic selection and contingency planning, recognizing that ideal pharmacology must fit into a patient’s life to achieve sustained benefit outcomes.
